Anion Gap Calculator with mEq/L readings and Significance
What the Anion Gap Calculator Evaluates
An anion gap is a useful result derived from an electrolyte panel that aids in check acid-base balance and spot possible reasons of metabolic acidosis. An anion gap calculator uses routine blood chemistry values to calculate the difference between routinely measured cations and anions, especially serum sodium and serum chloride, with serum bicarbonate as part of the formula.
The outcome is reported in mEq/L, short for milliequivalents per liter. This unit indicates charge concentration and is central to understanding serum electrolytes in a way that goes beyond looking at each number separately. Because the body contains many unmeasured anions and cations, the anion gap acts as a clinical tool that can reveal patterns not obvious from the raw lab values alone.
Clinically, the anion gap helps clarify the cause of an acid-base disorder. For example, a elevated gap may point to accumulation of acids, while a normal gap with low bicarbonate can point toward bicarbonate loss or a compensatory chloride increase. In practice, the calculator is most helpful when viewed alongside the full clinical picture, including symptoms, medications, and other laboratory results.
Anion Gap Formula in mEq/L
The standard anion gap formula is written as:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some providers also include potassium in the formula:
Anion gap = sodium + potassium - (chloride + bicarbonate)
Both approaches present the result in milliequivalents per liter, but the sodium based formula is used more often because potassium contributes relatively little to the final value. An anion gap calculator may use either version depending on its setup, but the key inputs remain the same: serum sodium, serum chloride, and serum bicarbonate, with optional potassium.
This works because plasma must remain electrically neutral. If the measured positive charge from sodium is much higher than the measured negative charge from chloride and bicarbonate, the difference reflects other ions https://anion-gap-help655.capitaljays.com/posts/what-disorders-lead-to-a-low-anion-gap not directly reported on the standard panel. That is why the anion gap is so helpful in evaluating metabolic acidosis and distinguishing high anion gap acidosis from normal anion gap acidosis.
In everyday use, the formula is simple, but its interpretation is more complex. A bicarbonate decrease may occur in various acid-base conditions, and the corresponding shift in chloride or other ions can change the calculated result. This makes the formula a starting point for clinical interpretation, not the final answer.
Using the Anion Gap Calculator
When you want to calculate the anion gap with an anion gap calculator, enter the results from the patient’s chemistry report. The main calculator inputs are:
Sodium level Cl value Serum bicarbonate Potassium, when the calculator uses it
After the values are added, the calculator returns the anion gap in mEq/L. That is especially valuable when assessing an electrolyte panel quickly, for example when evaluating a patient with possible metabolic acidosis, unexplained illness, or a suspected electrolyte disturbance.
For optimal accuracy, use values from the same specimen and the same lab draw whenever possible. Using values from different time points can distort the result and weaken the value of the calculation. In addition, be sure the units match the expected format. Anion Gap Calculator assumes the lab values are reported in conventional chemistry units that can be interpreted as milliequivalents/L for the purpose of the formula.
Once the result is displayed, compare it with the lab’s expected range. The calculator may flag a low, normal, or high result, but the meaning depends on the full context, including albumin level, acid-base status, and whether other abnormalities are present.
Normal Anion Gap Range and Expected Values
The normal range for the anion gap is influenced by the lab and the method used. A common reference interval may be around 8 to 12 mEq/L when potassium is excluded, though some laboratories report slightly different values. For this reason, it is important to use the specific lab’s reference range rather than relying on a single universal cutoff.
Technique differences matter. The same patient sample may produce different results depending on the analyzer, the measurement technique, and the lab’s calibration. This is one reason laboratory variation can affect how an anion gap is interpreted. A value that appears borderline in one setting may be completely expected in another.
Albumin also influences the expected range. Since albumin is a major unmeasured anion, lower albumin levels tend to lower the anion gap. That means a “normal” result may not always be reassuring if low albumin is present. In such cases, the apparent normal value can hide an elevated gap after adjustment.
Because of this, the raw number should be viewed as one piece of the larger acid-base puzzle. A gap within the reference interval does not automatically rule out disease, and a slightly elevated value does not always mean a major pathologic process is present. The clinical context and the rest of the blood chemistry are essential.
High Anion Gap Origins
A elevated anion gap is most often associated with build-up of acids in acid-base imbalance. This pattern suggests that unmeasured anions are rising, generally because acid is being added to the body or because acid clearance is impaired. A common approach is to think in terms of elevated anion gap acidosis and then look for the underlying source.
Many of the most common causes include:
Lactic acidosis, which can occur when tissues are underperfused or oxygen delivery is impaired Ketoacidosis, including diabetic, alcoholic, or starvation-related forms Renal failure, where the kidneys cannot remove acid effectively
Lactic acidosis raises acid load and can rapidly raise the anion gap. Ketoacidosis results in the buildup of ketone bodies, which are unmeasured anions. In renal failure, the body holds onto acids that would normally be excreted, steadily shifting the acid-base balance toward a higher gap.
Other causes may also be involved, including toxin exposures, severe illness, or marked disruption of metabolism. The key point is that a high gap often suggests that the body has gained acids or lost the ability to clear them. That makes the result useful as an early clue, but not as a final diagnosis.
Normal Anion Gap Metabolic Acidosis Causes
Not all acidosis is associated with a high gap. A standard anion gap pattern, often termed normal anion gap acidosis, usually suggests loss of bicarbonate rather than increase of unmeasured acids. This pattern is often described as hyperchloremic metabolic acidosis because the fall in bicarbonate is matched by a corresponding rise in chloride.
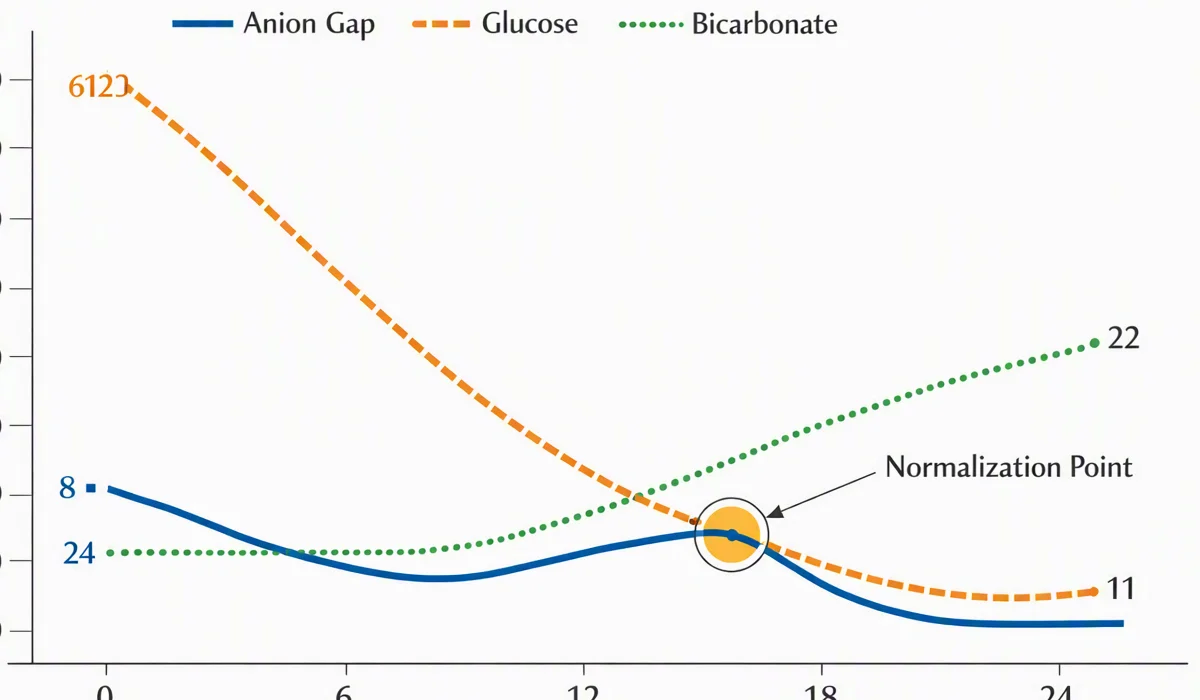
Common causes include diarrhea, renal tubular acidosis, and other forms of gastrointestinal loss. In diarrhea, bicarbonate is lost through the digestive tract. The body may compensate by retaining chloride, creating the classic hyperchloremic pattern. In renal tubular acidosis, the kidneys are unable to acidify the urine properly or do not reclaim bicarbonate adequately, again producing a normal gap acidosis.
This pattern is clinically important because the lab values can appear fairly normal except for the bicarbonate and chloride changes. A patient may have low bicarbonate, a normal anion gap, and significant symptoms. Spotting the pattern helps distinguish bicarbonate loss from acid accumulation.
In practice, the presence of a normal gap does not mean the patient is fine. It simply suggests a different mechanism. That is why reviewing the full electrolyte panel and the clinical story is essential.
Protein Adjustment and Adjusted Anion Gap
Albumin adjustment is an essential step when low albumin is present. Since serum albumin adds significantly to the unmeasured anions in blood, a low albumin level can make the measured anion gap look artificially low or normal. In these situations, the corrected anion gap provides a clearer reflection of the patient’s acid-base state.
A common correction formula applies a set amount to the measured gap for every decrease in albumin below normal. Different institutions may use slightly different adjustment methods, but the concept is the same: lower albumin means the expected baseline anion gap should be lower, so the measured result needs to be raised to avoid missing hidden acidosis.
This is especially helpful when the clinical picture suggests acid accumulation but the raw anion gap is not strikingly elevated. For example, a patient with low albumin may still have clinically important metabolic acidosis even if the uncorrected number seems only mildly abnormal. In such cases, the corrected anion gap can reveal a problem that would otherwise be overlooked.
Using albumin correction does not replace the rest of the workup. It simply improves the interpretation of the anion gap in patients with altered protein status, including those with chronic illness, inflammation, liver disease, or malnutrition.
How to Interpret the Result
Interpreting the value requires more than describing it as normal. Careful clinical interpretation starts by asking whether the result fits the patient’s symptoms, the rest of the laboratory values, and the likely acid-base disorder. A somewhat elevated gap may be important in one context and less concerning in another.
If the anion gap is increased, think about metabolic acidosis from acid accumulation. If the gap is not elevated but bicarbonate is low, consider normal anion gap acidosis, chloride-driven changes, or bicarbonate loss. If the result is surprisingly normal in a sick patient, consider albumin correction, a mixed picture, or a timing issue with the blood draw.
It also helps to check the full electrolyte panel for clues such as:
Reduced bicarbonate with higher chloride Unusual sodium shifts Potassium abnormalities Indicators of electrolyte imbalance across multiple values
A useful way to think about the result is as a pattern-based aid. The anion gap does not diagnose the cause by itself, but it helps differentiate likely mechanisms and directs the next step in evaluation. That is why it remains a practical part of blood chemistry review in many settings.
Frequent Limitations of an Anion Gap Calculator
Even a carefully built anion gap calculator has limitations. One major issue is measurement error. Tiny differences in sodium, chloride, or bicarbonate can noticeably change the final result, especially when the number is near the cutoff between normal and abnormal. Because of this, slight changes should be interpreted carefully.
The lab method used to measure electrolytes can also affect the calculation. Different analyzers may produce slightly different sodium or chloride values, which shifts the anion gap. That is one reason the reference interval should always come from the same laboratory that produced the patient’s results.
A further drawback is that the formula only accounts for a fraction of blood charge balance. Many important ions are not directly reported. As a result, unmeasured ions such as particular acids or toxins can change the gap without being obvious from the standard panel. Similarly, a patient may have a seemingly normal result while still having a important mixed acid-base disorders picture.
A mixed disorder can obscure the expected pattern. For example, a high gap acidosis might occur alongside a metabolic alkalosis or a normal gap acidosis, leading to a unclear or misleading number. This is why the anion gap calculator should be used as part of a more comprehensive assessment rather than as a stand-alone verdict.
Common Questions
What does an anion gap calculator do?
An anion gap calculator is used to calculate the anion gap from routine blood chemistry values and help interpret acid-base balance. It is most helpful for evaluating metabolic acidosis, detecting a possible high anion gap, and seeing when a normal anion gap pattern suggests bicarbonate loss or chloride-related changes.
How is anion gap calculated in mEq/L?
To calculate anion gap in mEq/L, apply the formula: serum sodium minus the sum of serum chloride and serum bicarbonate. Some versions also include potassium. The result is expressed in milliequivalents per liter, which shows the balance of measured ions in the blood.
What is a normal anion gap range?
The normal range depends on the lab and its reference range. A common reference interval is around 8 to 12 mEq/L when potassium is not included, but lab variation can shift that value. Always interpret the result using the laboratory’s own standards.
Why do you adjust the anion gap for albumin?
You modify the anion gap for albumin because serum albumin is a major unmeasured anion. In hypoalbuminemia, the measured gap can seem falsely low or normal. Using a correction formula offers a more accurate corrected anion gap and helps avoid overlooking hidden acidosis.
What does a high anion gap mean?
A high anion gap usually means there are additional unmeasured acids in the blood, which points toward metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, and renal failure. The result should always be interpreted alongside symptoms, the full electrolyte panel, and other laboratory values.