How to Work with an Anion Gap Calculator for Interpreting a Metabolic Panel
An Anion Gap Calculator is a practical aid for interpreting an anion gap result on a metabolic panel. It aids in turning common laboratory values into a helpful diagnostic clue for reviewing acid-base balance, especially when a clinician is reviewing an electrolyte panel for signs of metabolic acidosis or related acid-base disorder patterns.
With correct use, the calculator does much more than give a number. It helps relate serum sodium, serum chloride, and serum bicarbonate to the overall picture of metabolic panel interpretation. That means it can assist with recognition of a high anion gap, a low anion gap, or results that need follow-up with additional testing.
Understanding the Anion Gap Indicates
The anion gap is an estimate of the imbalance between measured positively charged and negatively charged electrolytes in the blood. In daily practice, it mainly shows the relationship between sodium, chloride, and bicarbonate. Because not all charged particles are directly measured, the anion gap offers an indirect picture at the presence of unmeasured ions and unmeasured anions.
In simple terms, the anion gap helps identify whether something is affecting acid-base balance. A normal result implies that the measured cations and anions are in normal balance, while an abnormal result may indicate an underlying acid-base disorder. This is why the anion gap is a standard part of metabolic panel interpretation in many settings.
Although the number is derived from routine chemistry tests, its clinical significance is much wider than the formula itself. A change in the anion gap can be a diagnostic clue that prompts a more detailed anion gap clinical significance metabolic acidosis evaluation, review of medications, or follow-up testing such as a blood gas.
How to Calculate the Anion Gap
An Anion Gap Calculator simplifies the process of calculate anion gap from values from the basic metabolic panel or comprehensive metabolic panel. The most widely used anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Some labs may use different formulas, especially if potassium is included. However, the sodium-based version is the most common in everyday interpretation.
To use the calculator, enter the patient’s serum sodium, serum chloride, and serum bicarbonate. The result estimates the gap between measured cations and anions. If the number is higher than expected, it may indicate extra unmeasured anions. If it is lower than expected, the result may reflect low albumin, lab variation, or another less common cause.
The calculator is especially helpful when reviewing a electrolyte panel quickly. For example, a low bicarbonate with normal chloride may suggest metabolic acidosis, while a low bicarbonate with a markedly elevated anion gap suggests a high gap acidosis.
It is important to remember that the calculator is only one step in clinical reasoning. It supports, but does not replace, a full assessment of symptoms, history, medications, and the rest of the lab pattern.
Normal Anion Gap Intervals and What Influences Them
The normal range for the anion gap is determined by the assay method and the lab’s normal interval or laboratory reference range. Since different laboratories measure ions differently, a result that is “normal” in one setting may sit slightly outside the range used elsewhere.
This variation is one reason clinicians should always interpret the number in context rather than relying on a single cutoff. The lab’s stated reference range is the most useful guide for that specific result.
Albumin has a major effect on the anion gap because it is a negatively charged protein and contributes substantially to the pool of unmeasured anions. When albumin is low, the anion gap may appear falsely reduced even if an acid-base problem is present. This is where correction for albumin becomes important.
An corrected-for-albumin or albumin-adjusted anion gap estimate adjusts for reduced albumin so the result better reflects the true acid-base picture. In practical terms, if albumin is low, the corrected value may reveal a hidden elevation that would otherwise be missed. This helps reduce the risk of a spuriously low anion gap.
Albumin adjustment is especially helpful when the patient has illness, inflammation, malnutrition, liver disease, or fluid overload—situations where albumin may be below the usual range. In those cases, the raw result may not fully represent the patient’s actual acid-base status.
High Anion Gap Acidosis Causes
A elevated anion gap is most often associated with metabolic acidosis. This happens when acids accumulate in the blood and increase the amount of unmeasured anions. The bicarbonate level frequently falls because it is being used to buffer acid, and the anion gap increases as a result.
Frequent causes of elevated anion gap include:
Lactic acidosis, which can occur when tissues are poorly perfused or under marked metabolic strain Ketone-related acidosis, including diabetic or fasting-related forms Kidney failure, where the kidneys cannot remove acid effectively Exposure to certain toxins or drugs that generate or hold onto acids
Lactate buildup is a classic cause of increased gap results and frequently signals tissue hypoxia, sepsis, or other conditions that limit oxygen delivery or utilization. Ketone-related acidosis usually appears with high ketones and may be seen in diabetes, prolonged fasting, or heavy alcohol use. Kidney failure adds to the problem by reducing acid excretion and allowing acid metabolites to build up.
When the calculator returns a high value, the next step is not just to label it outside the Additional info normal range. The key is to connect it to the patient’s overall clinical picture. For example, a low bicarbonate with a high anion gap clearly suggests a high gap acidosis pattern, but the exact cause still requires focused evaluation.
In many cases, the anion gap is a first step for a structured workup. Depending on the context, that may include lactate, ketones, creatinine, toxicology testing, and a blood gas to assess pH and compensation.
Reduced Anion Gap Causes and Clinical Relevance
A reduced anion gap is less common than a high one, but it can be medically significant. The most frequent explanation is hypoalbuminemia, since albumin is a key unmeasured anion. When albumin falls, the measured gap may drop even if the patient’s acid-base status is otherwise unchanged.
Additional notable causes include multiple myeloma, lithium exposure, and paraproteinemia. These conditions can decrease the calculated gap by adding positively charged proteins or cations into the system, shifting the balance of measurable ions.
Multiple myeloma and other paraproteinemia states can create abnormal proteins that influence the result. This is why an unexpectedly low number should not be ignored automatically. It can be a clue to a broader diagnostic process, especially if the patient also has anemia, kidney dysfunction, bone pain, or elevated total protein.
Lithium is another notable cause because it is a cation that can affect the calculation. In the correct clinical setting, a low anion gap may provide an earliest warning sign of lithium effect or toxicity.
As with a high result, a low value requires interpretation. A low gap may be due to true disease, but it can also reflect a measurement issue or a misleading result from low albumin. Accounting for albumin and reviewing the full chemistry panel supports interpretation.
How to Understand Results for a Metabolic Panel
Effective metabolic panel reading begins with the trend, not the result alone. The anion gap should be read alongside acid-base balance, sodium, chloride, bicarbonate, and the patient’s current status. A full interpretation often reveals whether the problem is an electrolyte disturbance, an acid accumulation state, or a blend of both.
For instance, a low bicarbonate with elevated chloride may suggest a normal-gap acidosis with a shift in chloride. In that scenario, the body may be exchanging bicarbonate loss for chloride gain, keeping the anion gap within range even though acidosis is present. By contrast, low bicarbonate with a high anion gap points more toward acid accumulation from causes such as lactic acidosis, ketoacidosis, or renal failure.
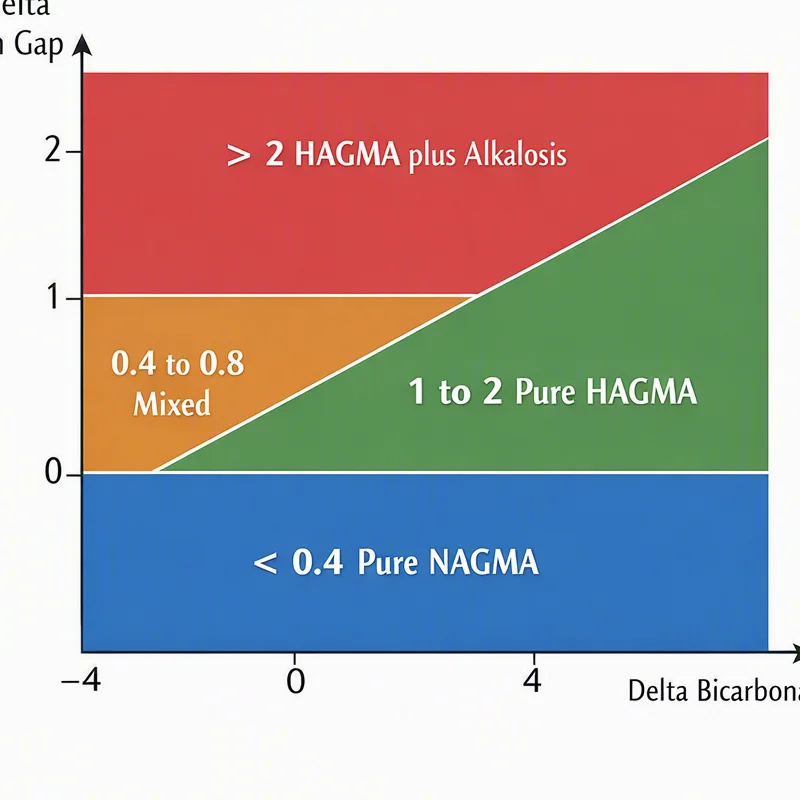
The shift in chloride is important because chloride often rises as bicarbonate falls in certain forms of acidosis. That means a patient can have clear acid-base disruption even when the anion gap is not elevated. This is why the calculator should be used as part of a broader review of the entire electrolyte profile.
One practical approach is to interpret results in this order:
Check sodium, chloride, and bicarbonate for clear abnormalities Use the Anion Gap Calculator to detect a high or low pattern Consider whether albumin may require correction Align the pattern with likely causes and symptoms Decide whether additional testing, including a blood gas, is needed
This method improves the chance of identifying the correct acid-base abnormality and makes the result more useful than a standalone calculation. The anion gap is best viewed as a practical bridge between raw laboratory values and a diagnosis that explains what is happening physiologically.
Drawbacks, Errors, and When to Repeat
Although a correctly used calculator has constraints. One common issue is laboratory error. A specimen problem, sample contamination, or analyzer issue can produce a misleading value. When the number does not fit the clinical picture, repeat testing is often the best next step.
Another pitfall is failure to account for unmeasured acids or protein-related effects. If albumin is low, the raw number may underestimate the severity of the underlying disturbance. If a patient has abnormal proteins or unusual cation exposure, the result may be shifted in the opposite direction.
A blood gas can be useful when the chemistry panel and symptoms do not align. It provides pH and respiratory compensation data, which can clarify whether the issue is truly metabolic, respiratory, or mixed. In patients with severe illness, the blood gas may also help confirm the urgency of the finding.
Recheck the result when:
The result conflicts with the patient’s condition The specimen may have been handled poorly Albumin levels are off and correction has not been applied There is worry for a hidden acid-base problem Treatment is underway and response needs confirmation
In short, the calculator is helpful, but it should not be treated as the final answer. A careful recheck can prevent misclassification and help distinguish a true abnormality from a transient or artifactual finding.
Frequently Asked Questions
What is an Anion Gap Calculator used for?
An Anion Gap Calculator is used to help interpret a metabolic panel by estimating the difference between measured electrolytes and identifying possible acid-base abnormalities. It is especially helpful for spotting a elevated anion gap or decreased anion gap pattern and for guiding next-step clinical reasoning.
How do you calculate the anion gap from a metabolic panel?
The standard anion gap formula is sodium - (chloride + bicarbonate). This calculation uses values from a BMP or comprehensive metabolic panel. Many clinicians use a calculator to make this faster and reduce arithmetic errors.
What’s a normal anion gap range?
The lab reference interval differs by lab because different instruments and methods can shift the result. For that reason you should use the lab’s stated normal range or lab reference range rather than using one single cutoff.
Why would the anion gap be high or low?
A high anion gap often indicates acidosis from causes such as elevated lactate, ketotic acidosis, or kidney failure. A low anion gap is often linked to low albumin, but it can also occur with multiple myeloma, lithium therapy, or paraprotein excess.
Is albumin adjustment necessary when interpreting the anion gap?
Absolutely, when serum albumin is low, albumin adjustment can refine interpretation and show a more accurate albumin-corrected anion gap. This is significant because hypoalbuminemia can make the gap look lower than it really is, leading to a false low anion gap and a missed diagnostic clue.