Anion Gap Calculator Using Blood Chloride Values
How the anion gap Is Measured
The gap calculation is a computed value that enables clinicians and people determine whether the body’s electrolytes are balanced and whether an acid-base status problem may be evident. It doesn’t measure a single substance directly. Instead, it infers the difference between standardly measured positive and negative ions in the blood, which can reveal clues about hidden acids or other unmeasured acids.
An anion gap calculator method is a helpful diagnostic aid because it turns routine blood chemistry results into a useful number for interpretation. When the anion gap is above or below the expected range, it can indicate a metabolic acid buildup, a different acid-base problem, or another metabolic change that requires closer evaluation.
The calculation is usually based on a standard electrolyte test panel, especially the sodium level, chloride value, and blood bicarbonate level. These laboratory values give a fast snapshot of the chemical environment in the bloodstream. Because the result is indirect, it should always be read in medical context, not as a stand-alone diagnosis.
How the Anion Gap Calculator Works
A device that uses blood chloride input generally asks for the patient’s serum sodium, serum chloride, and serum bicarbonate. These 3 measurements are enough to calculate anion gap in the most common way. The tool then calculates the gap between major measured cations and anions, which can show whether extra acids or other charged particles may be present.
In simple terms, the tool matches the sodium concentration against the combined effect of chloride and bicarbonate. This is why the accuracy of the chloride level matters so much. If chloride is unexpectedly high or low, the result can shift meaningfully, sometimes changing the impression from a normal anion gap pattern to a high anion gap or the reverse.
This type of anion gap calculator is particularly useful helpful when reviewing a serum chemistry report swiftly. It acts as a connector between raw laboratory values and bedside reasoning, giving a prompt estimate that can support broader clinical decision-making. Still, the calculator is only one part of the assessment; the numbers must be matched with symptoms, history, and other laboratory values.
Equation for Calculating Anion Gap
The classic anion gap formula reads:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
This calculation uses serum sodium as the principal measured cation and serum chloride plus serum bicarbonate as the primary measured anions. The remaining difference indicates the balance of other ions not routinely measured in a routine panel.
Many clinicians use this number as a clue to the presence of unmeasured anions. For example, if the gap is elevated, it may suggest an accumulation of acids or acid-related substances. If the gap is lower than expected, it may reflect changes in albumin, chloride, or testing issues.
A calculator that uses blood chloride input is helpful because chloride is a key variable in the equation. Even small changes in serum chloride can change the final result. That renders the tool useful for reviewing an electrolyte panel, confirming a suspected acid-base issue, or helping explain why two similar serum chemistry reports may produce different interpretations.
Standard Anion Gap Range and Assessment
The usual range for anion gap depends on the laboratory technique and the reference range used by that lab. Various analyzers and measurement methods can yield slightly different results, so there is no single cutoff that applies everywhere. That is why the reported reference range from the lab should always be checked first.
A normal anion gap generally suggests that the major measured ions are in expected proportion and that no major accumulation of unmeasured acids is evident from the calculation alone. However, a normal value does not automatically mean everything is normal. Some acid-base problems may still be present, especially if the pattern of sodium, chloride, and bicarbonate suggests another issue.
A increased anion gap usually points toward additional acids in the blood, while a low anion gap is less common and may indicate changes in proteins, measurement issues, or unusual laboratory patterns. In all cases, the number should be interpreted alongside the patient’s symptoms, the electrolyte panel, and broader overall clinical picture.
How chloride input Matters
Blood chloride is not just a supporting value; it is essential to the result. Because chloride directly reduces the result in the anion gap formula, any increase or reduction in serum chloride can meaningfully affect the outcome. This is why an anion gap calculator that specifically requires chloride input can provide clearer insight than a basic explanation of the formula.
When chloride is high, a pattern called hyperchloremia may appear. This can shrink the calculated gap and sometimes mask a concurrent acid-base process. When chloride is low, or hypochloremia is present, the gap may go up or appear less straightforward to interpret. These chloride-related shifts are a reminder that the calculator reflects a balance, not an independent disease diagnosis.
For this reason, reviewing the chloride value alongside sodium and bicarbonate helps determine whether the result reflects true physiology or just a change in one component of the electrolyte panel. In practice, the chloride level often provides the hint that makes the interpretation more precise.
Typical Causes of an Elevated Anion Gap
A increased anion gap typically points to a accumulation of acidic substances that are not measured directly in the standard electrolyte panel. One frequent cause is lactate-related acidosis, which can occur when tissue oxygen clinical use of AG delivery or utilization is impaired. Under these conditions, lactate increases and the anion gap rises as the body’s acid-base balance shifts.
Another key cause is ketone-related acidosis. This may occur when the body produces excess ketones, which act as unmeasured acids. The calculator can help flag this pattern, but the result must still be paired with blood glucose, symptoms, and other findings. A rising gap in this context often reflects a substantial metabolic disturbance.
Renal failure is also a classic cause of elevated gap values because the kidneys are less able to excrete acid and maintain normal electrolyte balance. As waste products accumulate, the anion gap may increase. In these scenarios, the calculator is best used as an initial hint rather than a final answer.
Typical Causes of a Low or Unremarkable Anion Gap
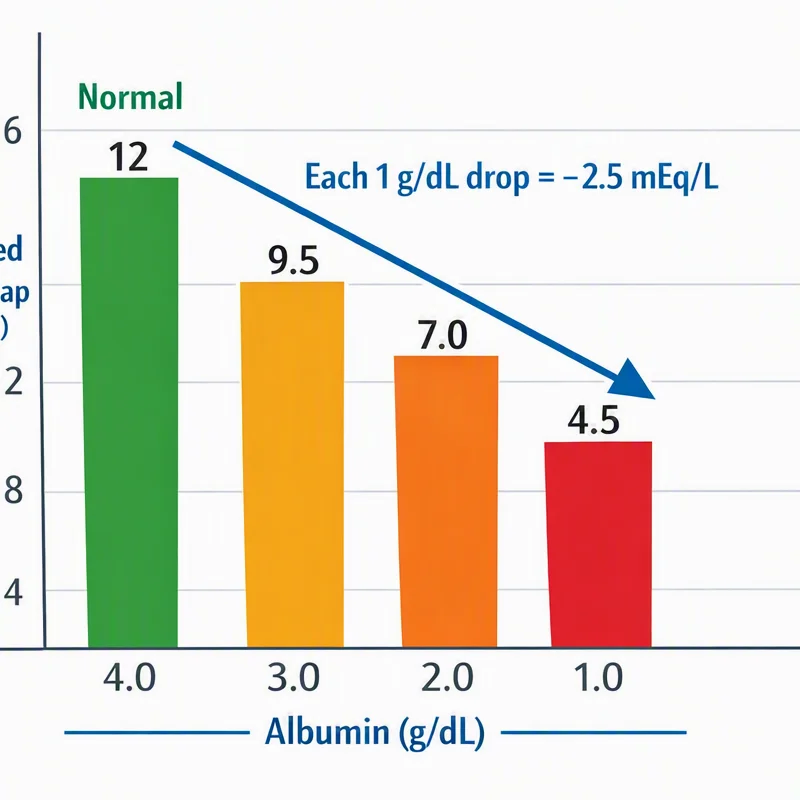
A reduced anion gap is not as common than an increased one, but it can be important in practice. One major cause is hypoalbuminemia, since albumin is a negative-charged protein that contributes to the normal gap. When albumin falls, the calculated number may drop even if there is an existing condition present.
Lab error should also be kept in mind whenever the result seems out of line with the clinical picture. Because the anion gap depends on several measured values, small problems in sodium, chloride, or bicarbonate reporting can alter the final value. That is why repeat testing or confirmation may be useful when the number does not fit the patient’s condition.
Multiple myeloma can sometimes produce a low anion gap because abnormal proteins may disturb the balance of charged particles in the blood. This is another example of why the result should be assessed as part of a full workup rather than as a standalone screening test.
How to Read Results in Clinical Context
Accurate interpretation begins with the raw numbers, but it does not end there. The most useful approach is to compare the result against the laboratory’s reference range, assess whether an acid-base disorder is present, and then review whether the pattern indicates a true metabolic acidosis or another imbalance.
Albumin correction is especially important when serum albumin is low. Since albumin contributes to the normal measured gap, a patient with hypoalbuminemia may appear to have a normal or low result even if hidden acids are present. A corrected anion gap can provide a better estimate of the underlying acid-base status in such cases.
The most effective approach is to combine the calculator result with the patient’s symptoms, history, and other laboratory values. anion gap clinical significance That is the essence of clinical correlation. A number that appears only mildly abnormal may be significant in one setting and less important in another. Likewise, a “normal” value may not exclude an evolving condition if the rest of the acid-base picture suggests a problem.
Limitations of an Anion Gap Calculator
Even a carefully built anion gap calculator has limits. The result depends on the lab’s reference range, which can vary based on analyzer type and reporting method. Different institutions may also define the normal window differently, so the same numeric result may be interpreted differently across settings.
Lab variability is another major issue. Small changes in how sodium, chloride, or bicarbonate are measured can affect the final answer. Because the formula subtracts two values from sodium, tiny analytical differences can have a noticeable effect. This is especially relevant when the result is close to the upper or lower limit of normal.
Measurement error can also create misleading results. A sample problem, analyzer issue, or transcription mistake may make the gap appear abnormal when it is not. For that reason, the calculator should be viewed as a first step for interpretation, not as definitive proof of disease. It is a helpful tool, but it cannot replace expert review of the full electrolyte panel and the patient’s clinical context.
Frequently Inquired
How do you determine an anion gap using blood chloride?
To work out the anion gap using blood chloride, apply the standard anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. An anion gap calculator does this automatically once you enter the serum sodium, serum chloride, and serum bicarbonate values from the electrolyte panel. The result helps estimate the balance of electrolytes and can aid in assessing an acid-base problem.
What is a high anion gap a sign of?
A high anion gap usually indicates there are additional acids or other unmeasured anions in the blood. Common causes include lactic acidosis, ketoacidosis, and renal failure. It is often a clue to metabolic acidosis, but the result should always be interpreted with the full clinical picture, not in isolation.
Can a normal anion gap still indicate a problem?
Yes. A normal anion gap does not completely rule out disease. Some acid-base disorders may still be present even when the calculated value falls within the expected reference interval. For example, changes in chloride, bicarbonate, or albumin can affect interpretation. That is why the electrolyte panel and overall clinical context are important.
How does albumin affect the anion gap?
Albumin is a major negatively charged protein in the blood, so it contributes to the normal anion gap. When albumin is low, the gap may appear lower than expected even if an acid-base disorder exists. This is why albumin correction and attention to serum albumin are important when reviewing results, especially in hypoalbuminemia.
When should an anion gap result be repeated or confirmed?
A result should be repeated or confirmed when it does not match the patient’s condition, when there is concern for lab error or measurement error, or when the value is borderline and affected by lab variability. Confirmation is also reasonable if the result is unexpectedly high, low, or inconsistent with other laboratory values. In those situations, reviewing the full electrolyte panel and repeating the test can improve confidence in the interpretation.