How Alcoholic Ketoacidosis Changes the Anion Gap
What Is the Anion Gap?
The anion gap is a laboratory calculation used to assist in identifying the reason of metabolic acidosis. It comes from the electrolyte panel and compares measured positively charged particles and negatively charged particles in the blood. In simple terms, it gauges the amount of unmeasured acid in the bloodstream.
A common formula uses sodium, bicarbonate, and chloride. The exact calculation may vary slightly by lab, but the basic idea is the same: if bicarbonate drops and unmeasured acids rise, the anion gap increases. That rise can signal an subtle acid-base disturbance that needs more workup.
An anion gap calculator helps clinicians and patients understand whether a result is inside the usual reference range or whether there is an anion gap elevation. Because albumin is a major unmeasured anion, low albumin can make the gap look falsely normal. That is why interpretation often requires a corrected anion gap, especially when the clinical picture suggests more serious disease.
What Is Alcoholic Ketoacidosis?
Alcoholic ketoacidosis is a serious metabolic emergency that usually occurs in people with heavy alcohol use who have had less food intake, repeated vomiting, or a combination of both. It often comes after a period of starvation or poor oral intake, when the body switches away from normal glucose use and starts breaking down fat for fuel.
This process creates ketones, including the ketone body beta-hydroxybutyrate, which can build up in the blood and result in ketonemia. The result is a form of metabolic acidosis driven by organic acids. Many cases also involve dehydration, hypovolemia, and nutritional stress, which can worsen the metabolic derangement.
Alcoholic ketoacidosis commonly appears in the setting of alcohol use disorder and may be accompanied by thiamine deficiency. Symptoms often include nausea and vomiting, abdominal discomfort, and a general unwell feeling, but the lab pattern is what usually points to the diagnosis.
Why Alcoholic Ketoacidosis Leads to a High Anion Gap
Alcoholic ketoacidosis leads to high anion gap metabolic acidosis because the body accumulates unmeasured organic acids, especially beta-hydroxybutyrate and additional ketone-related acids. These acids consume bicarbonate as they stabilize the blood, so bicarbonate falls while the gap widens.
As ketone production grows, the serum accumulates negatively charged acids that are not directly measured on the standard lab panel. Since the anion gap is based on the balance between sodium, bicarbonate, and chloride, a rise in unmeasured acids appears as a higher gap. This is why the anion gap is such a useful marker of acid-base balance.
Lactic acidosis may also play a role. People with alcoholic ketoacidosis can have poor tissue perfusion from dehydration and hypovolemia, which may increase lactate production. In addition, alcohol metabolism can alter redox balance and promote both ketone formation and lactate accumulation. The combination of ketones and lactate makes the acid load larger and can deepen the gap.
In practice, the elevated anion gap reflects a mixture of ketones, possible lactate, and other organic acids. That is why the lab pattern is usually classified as high anion gap metabolic acidosis rather than a single isolated abnormality.
How to Interpret an Anion Gap Calculator Output
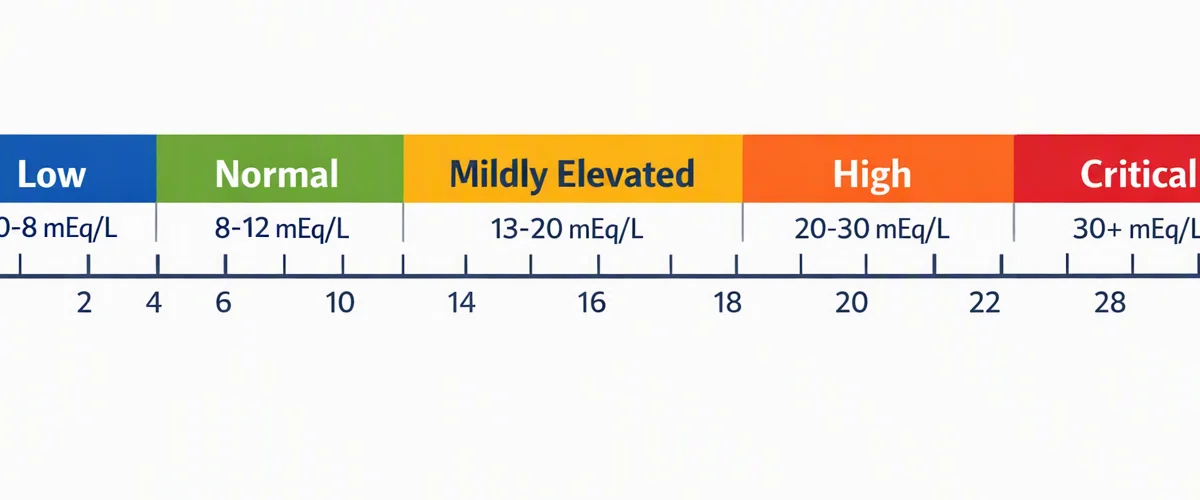
An anion gap calculator can be a practical first step, but the number must be understood in the full clinical picture. The calculator typically uses the input sodium, chloride, and bicarbonate values from the BMP. If the result is greater than the expected reference range, it indicates too much unmeasured acids.
One important issue is albumin. Because albumin is a major unmeasured anion, low albumin can obscure the degree of the problem. A patient with alcoholic ketoacidosis may have low albumin from poor nutrition or chronic illness, so the apparent anion gap may downplay the true acid load. In that case, a corrected anion gap gives a more accurate picture.
For example, if the uncorrected value seems only modestly elevated, but albumin is low, the corrected result may uncover important acidosis. This is especially helpful when comparing serial lab values and following whether treatment is resolving the metabolic acidosis.
Good lab interpretation also means taking into account what else is happening in the blood. A patient with vomiting may have a mixed acid-base picture: metabolic alkalosis from acid loss, plus high anion gap acidosis from ketones. That kind of mixed picture can make the calculator output look less dramatic than the clinical situation actually is.
Clinical Signs and Laboratory Results That Help Support Diagnosis
The signs can confirm the diagnosis and clarify why the anion gap is abnormal. A person with alcoholic ketoacidosis may have tachypnea as a form of respiratory compensation for the acidosis. The body attempts to lower carbon dioxide by breathing faster, which can partially offset the drop in pH.
Dehydration is frequent and may present with dry mucous membranes, weakness, dizziness, and reduced urine output. Because vomiting and poor intake are often present, the patient may also look volume depleted and ill. This may worsen kidney perfusion and make the acid-base disturbance more severe.
Glucose is another key clue. In alcoholic ketoacidosis, glucose may be low, normal, or only mildly elevated. That pattern helps separate it from other causes of ketoacidosis. Lab testing often shows elevated serum ketones and ketonemia, along with low serum bicarbonate and increased anion gap.
Supportive findings often include:
Marked high anion gap metabolic acidosis on the electrolyte panel Elevated serum ketones or strong evidence of ketonemia Low bicarbonate Dehydration with hypovolemia Tachypnea from respiratory compensation Possible hypoglycemia
These findings, combined with a history of alcohol use and poor oral intake, are highly suggestive of alcoholic ketoacidosis. The diagnosis is a clinical one supported by targeted labs rather than any one test.
How alcoholic ketoacidosis Differs from diabetic ketoacidosis
diabetic ketoacidosis and alcoholic ketoacidosis can both lead to ketosis and a high anion gap, but the pattern is often not the same. In diabetic ketoacidosis, the fundamental problem is severe insulin deficiency, which drives marked lipolysis and ketone production. In alcoholic ketoacidosis, the trigger is usually starvation, vomiting, and alcohol-related metabolic stress rather than lack of insulin.
Blood sugar is one of the most useful distinctions. diabetic ketoacidosis usually presents with clearly elevated blood glucose, while alcoholic ketoacidosis often has normal glucose or hypoglycemia. That difference can guide the differential diagnosis when the patient has metabolic acidosis and ketones.
Insulin also matters. In diabetic ketoacidosis, the lack of insulin is central, and treatment includes insulin therapy. In alcoholic ketoacidosis, the problem is not primarily an insulin deficiency, so treatment focuses on fluids, glucose, electrolytes, and nutrition support rather than routine insulin.
Both disorders involve ketone formation, but the context differs. Alcoholic ketoacidosis may have more pronounced vomiting, starvation, and dehydration, while diabetic ketoacidosis is more tightly https://anion-gap-estimator947.timeforchangecounselling.com/anion-gap-calculator-for-measuring-electrolyte-imbalance linked to uncontrolled diabetes. A careful clinical evaluation and lab profile are essential to avoid confusing the two.
Other Reasons of Increased Anion Gap Acidosis to Review
Alcoholic ketoacidosis is a important reason of increased anion gap metabolic acidosis, but it is not the only possibility. If the gap is elevated, the differential diagnosis should remain broad until the source is known.
Lactic acid buildup from lactate acidosis is a common other cause. This can occur in low perfusion, severe illness, tissue hypoxia, or seizure activity. Because alcoholic ketoacidosis can also include some lactate elevation, the two processes may overlap.
Alcohol toxins are another important concern. Consumption of substances such as methanol or ethylene glycol can produce severe acidosis and serious organ injury. These cases require rapid recognition because the treatment approach differs significantly from that of alcoholic ketoacidosis.
Renal failure can also increase the anion gap by impairing acid excretion and causing accumulation of unmeasured acids. Sepsis is another important cause because it can drive lactic acidosis and shock-related metabolic derangement. Because these conditions may present with comparable lab abnormalities, history and clinical context are crucial.
When reviewing an elevated anion gap, consider the full differential diagnosis:
Alcoholic ketoacidosis Diabetic ketoacidosis Lactic acidosis Alcohol toxins Renal failure Sepsis
When to Get Urgent Medical Care
This condition can turn serious fast, especially when vomiting, dehydration, or electrolyte losses are severe. Obtain prompt medical evaluation if there is confusion, fainting, chest pain, severe weakness, inability to keep fluids down, or worsening shortness of breath.
Hypotension is a warning sign that the patient may be significantly volume depleted or in shock. Marked electrolyte imbalance can cause heart rhythm problems, muscle weakness, and neurologic symptoms. These complications require prompt assessment, lab testing, and treatment.
A clinician may order repeat electrolyte testing, glucose, serum ketones, lactate, kidney function studies, and other tests depending on the situation. Because the condition can overlap with other emergencies, a timely medical evaluation is the safest approach when symptoms are significant or the patient appears unstable.
Initial care often includes fluid resuscitation, correction of glucose and electrolytes, and thiamine support when indicated. The exact treatment plan depends on the full clinical picture and the source of the acid-base disturbance.
FAQ: Alcoholic Ketoacidosis and Anion Gap
How does alcoholic ketoacidosis affect the anion gap?
Alcoholic ketoacidosis increases the anion gap because it causes buildup of unmeasured acids, especially ketones such as beta-hydroxybutyrate. As bicarbonate is consumed buffering those acids, the gap rises and produces high anion gap metabolic acidosis.
May alcoholic ketoacidosis happen with a normal glucose level?
Yes. Alcoholic ketoacidosis often occurs with normal glucose or even low glucose. That pattern helps distinguish it from diabetic ketoacidosis, where blood glucose is usually much higher.
How does alcoholic ketoacidosis different from diabetic ketoacidosis on lab tests?
Both can show metabolic acidosis, ketones, and an elevated anion gap, but diabetic ketoacidosis usually has much higher blood glucose and a primary insulin problem. Alcoholic ketoacidosis more often appears after vomiting, starvation, and poor oral intake, with normal or low glucose and significant ketonemia.
Does albumin change how you interpret the anion gap?
Absolutely. When albumin is low, it can make the anion gap look lower than it truly is because albumin is a major unmeasured anion. This is why a corrected anion gap is important when albumin is decreased or when the clinical picture suggests greater acidosis than the raw number shows.
What other conditions can cause a high anion gap besides alcoholic ketoacidosis?
Additional important causes include lactic acidosis, toxic alcohols, renal failure, sepsis, and diabetic ketoacidosis. If the anion gap is high, clinicians use the complete history, exam, and lab interpretation to refine the differential diagnosis and identify the correct treatment.