Anion Gap Calculator for Metabolic Alkalosis Review
What the Anion Gap Reflects
The anion gap is a calculated value that helps clinicians assess the difference between measured cations and measured anions in serum testing. An Anion Gap Calculator typically uses serum sodium, serum chloride, and serum bicarbonate from an basic electrolyte panel to determine whether there are extra, unmeasured anions found in the blood.
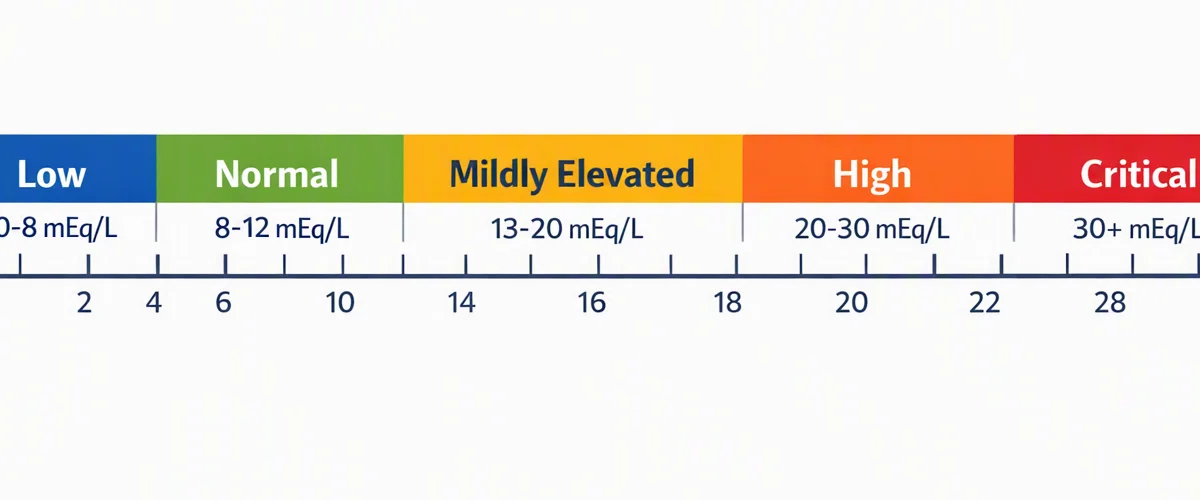
In plain language, the calculation gives a fast picture of acid-base balance. A change in the anion gap can indicate an underlying acid-base disorder, especially when laboratory values do not fully fit the patient’s symptoms or the expected body chemistry pattern.
The classic anion gap formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
Some clinicians and calculators also account for potassium, but most modern interpretation depends on sodium, chloride, and bicarbonate because the result is easier to standardize and use in clinical interpretation.
The value is useful because it may uncover whether there is an accumulation of unmeasured acids, whether there is a pattern of chloride depletion, or whether there may be a mixed acid-base disorder that would otherwise be overlooked on basic review of serum chemistry.
How to Use an Anion Gap Calculator
An anion gap calculator is no better than the data provided to it. Start with a current electrolyte panel and verify the values for sodium, chloride, and bicarbonate. Correct input matters because even small differences in these laboratory values can alter the final calculation and subsequent interpretation.
After entering the results, match the output to the local reference range. Reference intervals vary by laboratory method and analyzer, so a value that appears abnormal in one system may fall within range in another. This is why the same number should always be reviewed in the context of the reporting lab’s standard.
Albumin correction should be used whenever albumin is low. Because albumin contributes negatively charged protein anions, a low albumin level can make the measured anion gap appear misleadingly normal or low. Correcting for albumin enhances diagnostic accuracy and can uncover a clinically important elevation that was hidden by hypoalbuminemia.
A practical workflow is:
Check the electrolyte panel for sodium, chloride, and bicarbonate. Input the numbers into the anion gap calculator. Check whether the result fits the reference range. Review albumin and apply albumin correction if needed. Analyze the corrected anion gap alongside the patient’s symptoms and acid-base balance.
This approach is especially helpful in critical care and acute settings, where subtle shifts in serum chemistry can indicate major changes in physiology.
Metabolic Alkalosis Overview
This acid-base disorder is a fundamental acid base disorder characterized by an rise in blood bicarbonate and a corresponding increase in pH. An early sign is often seen on a blood pH above the expected range, with elevated serum bicarbonate on chemistry testing. To verify the pattern and assess compensation, clinicians often rely on an arterial blood gas.
An arterial blood gas provides a broader picture than the chemistry panel alone because it shows pH, carbon dioxide, and oxygenation. In metabolic alkalosis, the body typically responds through respiratory metabolic compensation, leading to a higher carbon dioxide level than expected. The base excess is also often positive, reflecting excess buffer in the system.
Understanding the pattern matters because metabolic alkalosis is not a diagnosis by itself; it is a physiologic finding that requires patient assessment and evaluation for the underlying etiology. A calculator can support the workup, but the clinical picture remains essential for safe interpretation.
In practice, a patient with vomiting, diuretic exposure, or volume loss may show elevated bicarbonate and alkalemia. Yet the anion gap can still provide insight, especially when the disorder is not isolated or when the expected laboratory pattern does not match the clinical situation.
Why the Anion Gap Still Counts in Metabolic Alkalosis
Although the anion gap is commonly discussed in relation to acidosis, it still plays a role in metabolic alkalosis. The reason is that alkalosis can coexist with another process that changes the anion gap, creating a mixed acid-base disorder. A patient may have alkalosis from vomiting and at the same time have an unrecognized high-gap acidosis from another cause.
For example, lactic acidosis can develop in patients with hypoperfusion, sepsis, or severe illness, while ketoacidosis may occur with diabetes, starvation, or alcohol-related metabolic stress. These processes elevate unmeasured anions and can raise the high anion gap even when bicarbonate is elevated from a separate alkalotic process.
That is why a normal-looking bicarbonate level or obvious alkalemia does not rule out a concurrent metabolic problem. In some patients, the apparent alkalosis masks a second disorder; in others, the opposing processes partially offset each other. Careful review of the anion gap helps uncover that hidden complexity.
Chloride depletion is yet another reason the anion gap remains clinically useful. When chloride is low, bicarbonate may rise to maintain electrical neutrality, which can produce a normal anion gap pattern or a value that appears only mildly abnormal. That context is important when determining whether the disorder is purely alkalotic or part of a broader acid-base disturbance.
Modifying the Anion Gap for Albumin
Hypoalbuminemia can significantly distort the measured anion gap. As albumin is a major negatively charged protein in plasma, a low concentration decreases the number of native protein anions available in the serum. The result can be a misleadingly low or normal anion gap even when excess acid is present.
That is why albumin correction is a crucial step in many cases. The corrected anion gap adjusts the raw value using a correction factor based on albumin level, enhancing the detection of hidden acid accumulation. This is particularly relevant when evaluating patients with poor nutrition, liver disease, inflammation, or critical illness.
A common clinical approach is to understand that for every decline in albumin, the measured anion gap decreases by a predictable amount. Applying a correction factor can reveal the true degree of acid burden and enhance diagnostic accuracy. Different institutions may use varied correction methods, so the key is to apply the method used by your laboratory or clinical protocol.
In metabolic alkalosis evaluation, albumin correction is helpful because the alkalotic state can coexist with an elevated gap process that would otherwise be underestimated. A corrected result gives a better basis for clinical interpretation and can shift the assessment toward a mixed acid-base disorder rather than isolated alkalosis.
Frequent Causes of Metabolic Alkalosis
The most frequent causes of metabolic alkalosis are often straightforward to memorize, but the physiologic mechanism matters. Emesis can deplete gastric acid and produce a net alkaline state. Diuretics can increase renal loss of sodium, chloride, and potassium, which encourages bicarbonate retention. Both processes may also contribute to fluid loss, which enhances renal reabsorption of bicarbonate.
Mineralocorticoid excess is an additional major cause. Excess aldosterone activity increases hydrogen and potassium loss in the kidney, leaving the blood relatively more alkaline. This pattern often appears with hypertension, hypokalemia, and persistent electrolyte imbalance.
Other causes may include nasogastric suction, bicarbonate administration, and post-hypercapnic states, but the main practical takeaway is that many causes of alkalosis also change sodium, chloride, and bicarbonate in ways that influence the anion gap calculation. Reviewing the full electrolyte panel helps determine whether the pattern is consistent with a single process or something more complex.
In a patient with vomiting or diuretic exposure, the anion gap may remain normal. However, if the history or exam suggests sepsis, poor perfusion, or diabetes, the possibility of an added high-gap process should be actively considered. That is where the calculator becomes part of a broader diagnostic approach rather than a stand-alone number.
Reading Values Step by Step
A structured method improves acid-base analysis. Start with the raw anion gap result, then compare it to the local reference range. Then, determine whether the pattern is low, normal, or high anion gap. Finally, connect that pattern to the patient’s acid-base status and likely cause of the electrolyte imbalance.
Step 1: Confirm the serum sodium, serum chloride, and serum bicarbonate values. If any result seems inconsistent, verify the sample and repeat testing if needed.
Step 2: Compute or review the anion gap using the calculator. This gives a rapid readout of whether unmeasured anions may be present.
3: Assess albumin and apply albumin correction if the level is low. A low albumin can hide a clinically relevant elevation.
Step 4: Decide whether the result suggests a normal anion gap alkalotic pattern, a high anion gap process, or a combination of disorders.
5: Interpret the result with the arterial blood gas, blood pH, and base excess. If the pH is alkalemic but the gap is elevated, a mixed acid-base disorder should be strongly considered.
6: Apply the clinical picture to identify the most likely cause, such as vomiting, diuretics, volume depletion, or mineralocorticoid excess, while also screening for lactic acidosis or ketoacidosis when appropriate.
This organized process supports stronger bedside decision-making and helps avoid false reassurance when the laboratory pattern appears deceptively simple.
When to Order Additional Tests
Further workup is appropriate when the anion gap result does not fit the overall presentation or when symptoms suggest a second process. If the patient appears sick, low in blood pressure, dehydrated, or has unexplained tachypnea, additional assessment is needed. The goal is to uncover any hidden metabolic stress alongside the alkalosis.
Serum lactate should be ordered when tissue hypoperfusion, sepsis, or hypoxia is possible because elevated lactate can indicate lactic acidosis. Ketones are important when diabetes, fasting, alcohol use, or altered mental status raises concern for ketoacidosis. These studies help determine whether a high-gap process is present even if the alkalosis seems dominant.
Renal function tests are also useful because kidney impairment can alter acid handling, bicarbonate retention, and the interpretation of serum chemistry. A rising creatinine or other renal abnormality can change the differential diagnosis and may explain electrolyte disturbances.
Urinalysis may provide additional clues, including ketones, hydration status, or urinary losses related to diuretic exposure and volume depletion. In selected cases, urine chloride can also help distinguish chloride-responsive from chloride-resistant alkalosis.
Arrange these tests sooner rather than later if the patient has severe symptoms, altered mental status, signs of shock, or an unexplained mismatch between pH, bicarbonate, and the anion gap.
Limitations of the Anion Gap in Metabolic Alkalosis
The anion gap is valuable, but it is not perfect. Lab variation between analyzers can shift the reference range, and measurement error in sodium, chloride, or bicarbonate can change the result enough to affect interpretation. Even a small analytical difference may matter when the value is borderline.
Another limitation is that the anion gap only reflects what is not directly measured. It does not identify specific acids or toxins by itself, and it cannot fully characterize every acid-base disorder. Instead, it serves as a screening and pattern-recognition tool that must be paired with the patient’s symptoms, exam, and other laboratory values.
Unmeasured anions can build up in many conditions, but the precise cause still requires directed workup. Likewise, a normal anion gap does not exclude a serious disorder if the patient has concurrent hypoalbuminemia or a mixed process. That is why clinical context is essential.
In metabolic alkalosis, a calculator should guide questions, not substitute for judgment. The best results come from combining the numerical output with history, physical findings, arterial blood gas results, and complete patient assessment.
Frequently Asked Questions
What is the anion gap formula used in an Anion Gap Calculator?
The standard anion gap formula is serum sodium minus the sum of serum chloride and serum bicarbonate. In most calculators, the result is based on the electrolyte panel and then compared with the reference range used by the lab.
Why can the anion gap be useful in metabolic alkalosis evaluation?
It helps detect a mixed acid-base disorder. A patient may have metabolic alkalosis from vomiting or diuretics and still have a concurrent high-gap process such as lactic acidosis or ketoacidosis. The anion gap adds another layer of acid-base interpretation.
How do you correct the anion gap for low albumin?
Use albumin correction when albumin is low to estimate the corrected anion gap. Because hypoalbuminemia lowers the measured gap, the correction helps reveal hidden excess acids. The exact correction factor may vary by institution.
Can metabolic alkalosis and a high anion gap occur together?
Yes. This can happen when a patient has metabolic alkalosis from one cause and lactic acidosis or ketoacidosis from another. In that situation, the acid-base picture is mixed, and the arterial blood gas, blood pH, and anion gap should all be reviewed together.
What additional tests should be ordered if the anion gap is abnormal?
Common next tests include serum lactate, ketones, renal function tests, and urinalysis. methanol AG and osmolar gap These studies help identify lactic acidosis, ketoacidosis, kidney-related abnormalities, or urinary clues that explain the electrolyte imbalance and overall clinical picture.